
Compounded preparations are dispensed only on a doctor’s prescription.
Short answer: In a 2024 placebo-controlled trial, 2 g of D-mannose daily for six months did not reduce clinically suspected UTIs in women with recurrent UTI (PMID 38587819). A 2025 meta-analysis found no reduction compared with control (PMID 41004704), while a 2014 trial reported a lower risk than no prophylaxis (PMID 23633128). Results are mixed.

Why this question usually starts with a doctor
The 2024 trial describes recurrent UTI as “a common debilitating condition in women, with limited prophylactic options” (Hayward et al., 2024; PMID 38587819). The question is one to settle with a doctor who has the full urinary history.
The studies below describe what D-mannose has been tested for and what the trials found. They do not replace a doctor’s assessment of your urinary symptoms, your history or your other medicines. Any compounded preparation is made for one named patient on a doctor’s prescription, under Good Compounding Practice (GCP).
What D-mannose is and how it has been studied
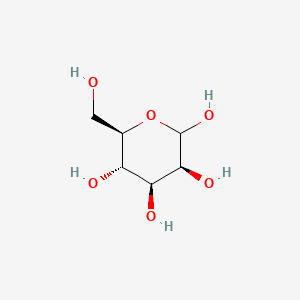
D-mannose is a sugar. Two of the three studies below used D-mannose powder at 2 g daily for six months (PMID 38587819, PMID 23633128). The 2025 meta-analysis pooled six randomised controlled trials (PMID 41004704). The findings describe the D-mannose products those trials tested.
What the trials and meta-analysis show
The table below lists each study with its design and population, dose and duration where the abstract states them, the outcome as reported, and PMID.
| Study | Design and population | Dose and duration | Outcome as reported | PMID |
|---|---|---|---|---|
| Hayward et al., 2024 | Double-blind randomised placebo-controlled trial; 303 women randomised to D-mannose and 295 to placebo, in UK primary care | 2 g daily of D-mannose powder for 6 months | 51.0% with D-mannose versus 55.7% with placebo contacted ambulatory care with a clinically suspected UTI (risk difference -5%, 95% CI -13% to 3%; P = .26) | 38587819 |
| Kranjčec et al., 2014 | Randomised trial of 308 women with recurrent UTI after treatment of acute cystitis; D-mannose, nitrofurantoin or no prophylaxis | 2 g of D-mannose powder in 200 ml of water daily for 6 months | Significantly lower risk of recurrent UTI than no prophylaxis (RR 0.239, P < 0.0001) | 23633128 |
| Vargas et al., 2025 | Systematic review and meta-analysis of six randomised trials with 1,167 participants, in patients at high risk of recurrent UTI | Dose not stated in the abstract | D-mannose was not associated with a reduction in recurrent UTI compared with control (RR: 0.57, 95% CI 0.29 – 1.15) | 41004704 |
The 2024 trial’s authors concluded that “daily d-mannose did not reduce the proportion of women with recurrent UTI in primary care who experienced a subsequent clinically suspected UTI”, and that “d-Mannose should not be recommended for prophylaxis in this patient group” (Hayward et al., 2024; PMID 38587819).
The 2014 trial reported that D-mannose powder “had significantly reduced the risk of recurrent UTI”, and that side effects in the active groups were “mild and did not require stopping the prophylaxis” (Kranjčec et al., 2014; PMID 23633128). Its authors also wrote that “More studies will be needed to validate the results of this study” (PMID 23633128).
The 2025 meta-analysis concluded that D-mannose “did not reduce the incidence of recurrent UTIs compared with control or antibiotics in high-risk patients” (Vargas et al., 2025; PMID 41004704).
What each design can and cannot show
The 2024 trial was double-blind and placebo-controlled. Of the 294 women in the D-mannose group with primary outcome data, 150 (51.0%) contacted ambulatory care with a clinically suspected UTI, against 161 of 289 (55.7%) on placebo (risk difference -5%, 95% CI -13% to 3%; P = .26) (PMID 38587819). The outcome was a clinically suspected UTI, which is contact with ambulatory care, not a laboratory-confirmed infection in every case. The confidence interval includes both a small benefit and a small harm, so the trial does not settle the question in either direction for its population.
The 2014 trial randomised 308 women with recurrent UTI and no other significant comorbidities, after treatment of acute cystitis, to D-mannose, nitrofurantoin or no prophylaxis (PMID 23633128). Its abstract reports that D-mannose powder “had significantly reduced the risk of recurrent UTI which was no different than in Nitrofurantoin group”. That comparison is with a single antibiotic, in a population defined by a recent acute cystitis episode.
The 2025 meta-analysis included six randomised controlled trials with 1,167 participants, in patients at high risk for recurrent UTI (PMID 41004704). Its conclusion covers both control and antibiotic comparators. A pooled estimate across six trials describes the group, not any one patient.
How to read the mixed results
The studies do not point the same way. The 2024 trial was placebo-controlled and enrolled eligible community women with a mean age of 58 years. The 2014 trial compared D-mannose with nitrofurantoin and with no prophylaxis, in women after treatment of acute cystitis.
Three designs, three populations and three comparators make the mixed picture hard to resolve from abstracts alone. A reader should not average the three results into one answer. The honest summary is that D-mannose has been studied in several designs, that results vary between trials, and that the 2024 placebo-controlled trial did not show a benefit in its population.
Limits of the evidence
The trials are few and differ in population. The 2014 trial enrolled women with no other significant comorbidities, and its authors asked for more studies to validate their results (PMID 23633128). The 2024 trial enrolled community women, and the 2025 meta-analysis pooled six randomised trials with 1,167 participants (PMID 41004704). The two trials that state a dose used 2 g daily for six months (PMID 23633128, PMID 38587819).
Decisions for patients with other conditions, such as kidney disease, pregnancy or diabetes, belong with the patient’s doctor. The trials describe the D-mannose products they tested, not compounded preparations, so their findings are not a result for any prepared formulation.
What to bring to the conversation with your doctor
- A record of your infections, with approximate dates, symptoms and any urine tests your doctor has ordered.
- Previous antibiotic courses, with the dates and whether each one was completed.
- Current medicines and supplements, and any kidney or diabetes history.
- Pregnancy plans or status, where relevant.
If you have had recurrent UTIs, bring the question to your doctor and go through the evidence above together. Do not start, stop or change a dose of any product without advice.
Our article on converting an overseas prescription into a Kuala Lumpur compounded equivalent explains how a doctor’s prescription is handled. Compounded preparations are made under Good Compounding Practice (GCP), as set out on our GCP laboratory page.
Reviewed by Vitthia Rama Murti, RPh (RPh 15632).
How to get this prescribed
Only a registered doctor can prescribe a compounded preparation. Ask your doctor whether D-mannose is suitable for you, whether a patient-specific preparation is the right route, or whether another option is more appropriate.
If a doctor decides a compounded preparation is appropriate, the prescription should state the active, the strength, the form, the quantity and the directions for use. Ask your doctor to send the signed prescription to Lynnity through our contact page. Vitthia Rama Murti, RPh (RPh 15632), can be contacted through the same page, and our pharmacists team page sets out the team.
Frequently asked questions
Has D-mannose been shown to reduce recurrent UTIs?
The evidence is mixed. A 2024 randomised placebo-controlled trial found no significant difference in clinically suspected UTIs at 2 g daily (PMID 38587819), and a 2025 meta-analysis found no reduction compared with control (PMID 41004704). A 2014 trial reported a significantly lower risk of recurrent UTI than no prophylaxis (PMID 23633128). The results differ between studies.
How much D-mannose did the trials use?
The 2014 and 2024 trials used 2 g daily for six months (PMID 23633128, PMID 38587819). The 2014 trial took the powder in 200 ml of water. The dose for any individual is a decision for the patient’s doctor.
Can D-mannose replace antibiotics for recurrent UTIs?
None of the studies cited here establishes D-mannose as a replacement for antibiotics. The 2025 meta-analysis reported that D-mannose did not reduce recurrent UTIs compared with control or antibiotics in high-risk patients (PMID 41004704). Any change to antibiotic use should be made with a doctor.
Is a compounded D-mannose preparation dispensed without a prescription?
No. Compounded preparations are dispensed only on a doctor’s prescription, prepared for one named patient under Good Compounding Practice (GCP). The prescription should state the active, strength, form, quantity and directions for use.